I love learning about technology that makes an ordinary part of the day suddenly seem much more complicated, and walking is a very good example. We decide to go somewhere, our legs move, and most of the time we're thinking about whatever we're going to do when we get there. Meanwhile, there's an enormous amount of communication happening between the nervous system, muscles, joints, and the ground beneath us. Japan's HAL exoskeleton caught my attention because it uses electrical activity detected at the skin to help with part of that movement, which is a remarkably interesting thing for a wearable machine to be able to do.
HAL stands for Hybrid Assistive Limb, and it comes from work led by Professor Yoshiyuki Sankai at the University of Tsukuba and the company Cyberdyne. Those names do have a certain science-fiction quality, although the part I'm most interested in happens in rehabilitation, with somebody trying to take a step and a team working out how to help. I spend plenty of time on my feet as a server, so I appreciate how easily walking becomes something we expect our bodies to handle while we're occupied with everything else. Learning about a machine built around the effort involved in moving gives me a reason to look a little more closely at what that familiar action requires.
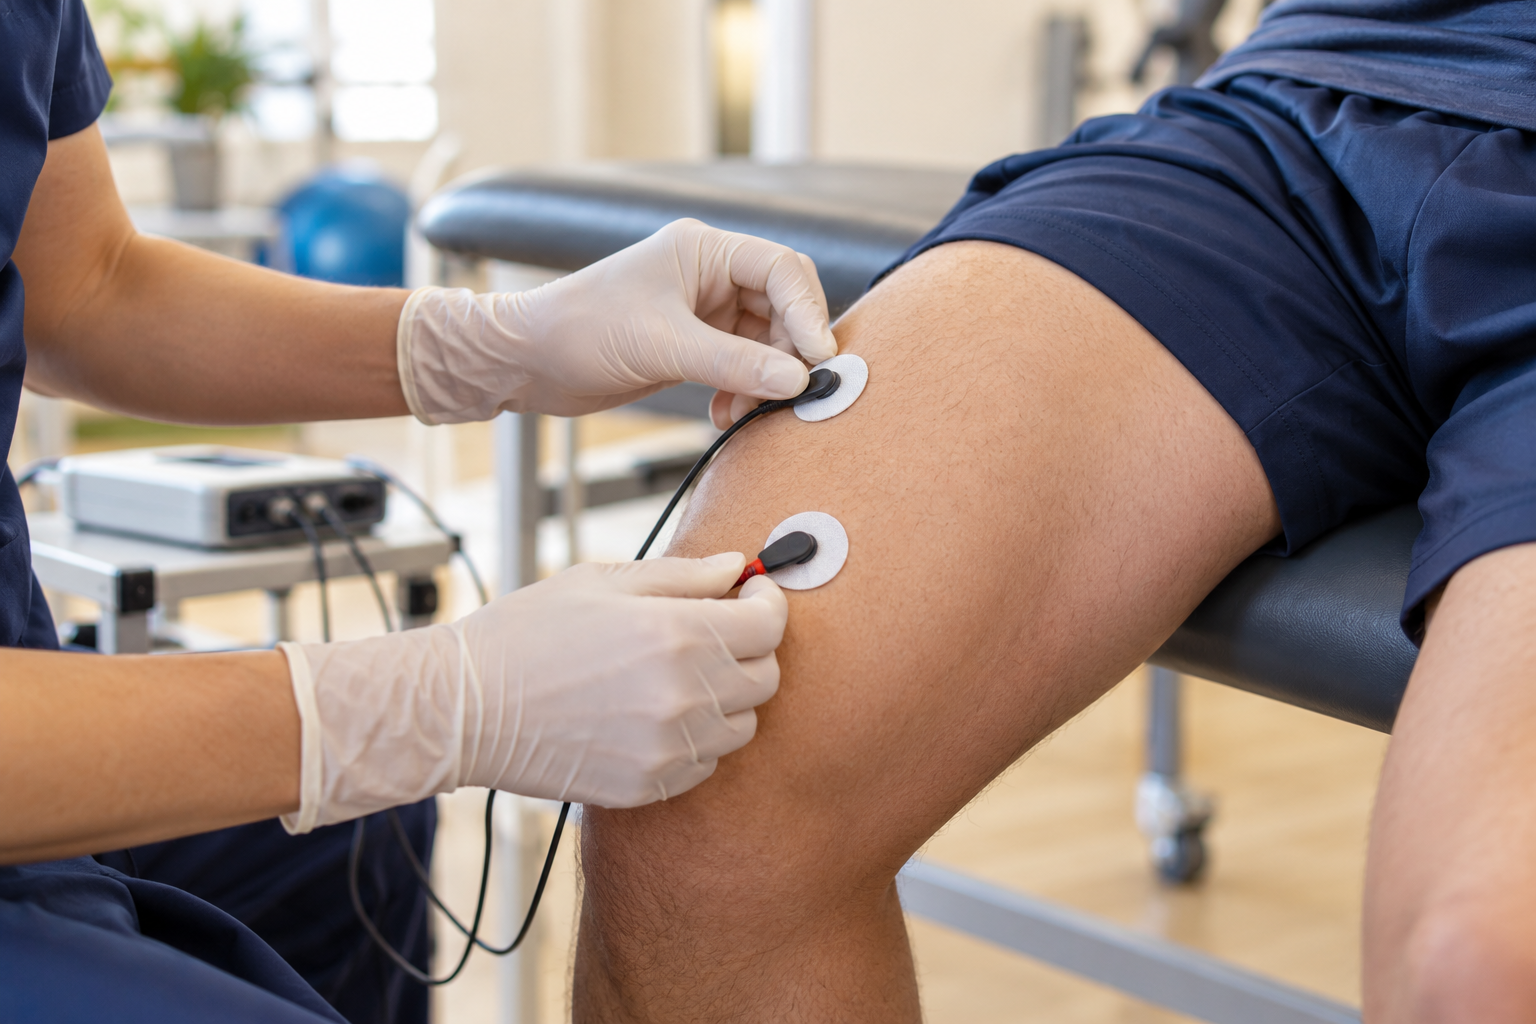
The Signals Are Picked Up Near the Muscles
When HAL is described as listening to the brain, it's easy to get the impression that someone puts on a robot and it reads a thought directly from their head. The medical lower-limb system uses surface electromyography, usually shortened to EMG, which records electrical activity associated with muscles through electrodes on the skin. In its voluntary-control mode, it uses signals from muscles involved in moving the hips and knees to help control powered assistance at those joints. The brain is part of the chain that produces voluntary movement, but the measurement is being made farther along that chain, at the body, rather than through a brain implant or a thought-reading headset.
That distinction actually makes the engineering more interesting to me, because a small signal can be useful even when the person has difficulty producing an effective movement. The system processes what it detects and uses that information to coordinate assistance with the wearer's effort. There has to be usable information to work with, and suitability depends on the person and the device being used. I like the idea that an effort which might be difficult to see from the outside can still give a machine something to respond to, without turning that into a promise that every injury leaves behind a signal HAL can use.
The Motors Still Have a Fairly Physical Job
The lower-limb exoskeleton fits around the legs and trunk, with powered joints helping provide the turning force needed at the hips and knees. A controller, sensors, and the supporting structure all have jobs to do, and a trained clinician adjusts the assistance. The FDA's technical description also distinguishes voluntary control from an autonomous mode that uses information such as posture and measurements from the sensor shoes. So the interesting part involves combining information about the person with the mechanical work of moving a joint, rather than asking one tiny electrical signal to do absolutely everything.
Once I start thinking about that combination, I get caught up in how particular a wearable robot has to be. Our legs have different lengths, our joints need room to move, and the piece of equipment has to work with the person wearing it. A robot standing on its own can be an impressive engineering project, but attaching one to somebody adds a whole collection of practical questions about fit, comfort, timing, and control. The ability to make an adjustment becomes part of the appeal, especially when the point of the session is to help a particular person practice a particular movement.
The Interesting Part Continues After the Step
Cyberdyne describes its treatment approach through a loop involving the wearer's attempt to move, the assistance HAL provides, and sensory information returning as the movement happens. The company calls this interactive biofeedback, and the idea is to pair voluntary effort with the experience of the intended movement during repeated practice. That gives us a useful way to understand why HAL is studied as part of rehabilitation, beyond the immediate sight of a powered frame helping a leg move. The wearer is participating, the machine is assisting, and the movement itself supplies information for the nervous system.
The question that really interests me is what someone can do after the equipment comes off, because assisted movement during a session and improved ability afterward are different things to measure. A good demonstration can show the first, while the second needs follow-up testing and a clear account of what changed. I can be excited about the possibility of useful improvements without calling every gain the regrowth of damaged nerves, which would be a much bigger biological claim. The actual work of helping someone practice movement is fascinating enough that I'd rather understand it properly than skip straight to the most dramatic description.

A Training Session Has People Behind the Equipment
At the University of Tsukuba, HAL research brings together people working in biomechanics, rehabilitation, neurosurgery, orthopedics, and cybernics, which gives a much better sense of the project than the image of an inventor working alone with a gleaming suit. The university's biomechanics lab describes investigating how movement changes and what neurological mechanisms might be involved in recovery. I like that combination of questions, because a machine can produce something worth measuring while researchers are still trying to understand the full explanation for what they're seeing. A useful device and a complete account of its effects don't have to arrive on the same afternoon.
It also makes me think about the people beside the wearer, whose work is much less obvious in a photograph of the robot. Somebody has to assess the person, help set up the session, make adjustments, and decide how the training fits with everything else they're doing. The suit gets the striking picture, while the person's effort and the team's decisions take place over considerably more time than a photograph can hold. If I were watching a session, I'd probably want to ask about those choices as much as the hardware, especially what the person hoped to make easier in their own day.
One Trial Measured Walking Distance Without the Suit
A trial published in the Orphanet Journal of Rare Diseases in 2021 tested HAL-assisted training in people with slowly progressive rare neuromuscular diseases. Thirty participants were randomly assigned to treatment sequences, and 24 were included in the final analysis. In the crossover design, they received walking programs with HAL and a supporting hoist, and programs using the hoist alone, with nine sessions in each treatment period. The main outcome was distance in a two-minute walking test, assessed without HAL. The percentage improvement favored HAL by about 10 percentage points, which gives us something much more specific to discuss than a general claim that a robot restored movement.
That result belongs to the patients and training program studied, and it doesn't tell us that everyone who wears HAL will walk independently afterward. The trial also recorded mild problems such as muscle or back pain and skin irritation, so comfort and monitoring belong in the story too. What I find encouraging is the effort to ask a measurable question about function beyond the device, especially for people living with conditions that can make walking increasingly difficult. A change in what someone can do deserves a clear description, even when the description is considerably less dramatic than the headline our imaginations would like to write.
Stroke Research Gives Us a Different Part of the Story
Results also depend on who is receiving the training and what it's being compared with. A randomized study published in PLOS ONE in 2020 involved 32 people with severe walking limitations in the subacute period after stroke, comparing rehabilitation that incorporated HAL with conventional gait training. Both groups improved, and the study found no significant difference between them in the assessed outcomes. The authors were interested in identifying which patients might benefit most from this kind of equipment, which seems a much more useful question than treating every person with a walking difficulty as though they need the same approach.
I think this is where a story about a robot can become a story about good rehabilitation more generally, because the comparison group contains people doing real work with real therapists too. Improvement after a course of treatment is worth celebrating, while understanding what the machine added helps decide how to use it. I'd want researchers to keep asking those questions as devices change and different groups are studied. It's possible to find the technology genuinely exciting and still want to know whether a particular person gains something useful from the extra equipment, setup, and time involved.

What the U.S. Clearance Actually Covers
HAL has moved beyond a university demonstration, and its medical use has a specific regulatory history. The FDA's May 2024 clearance for Medical HAL Lower Limb Type covers gait training for defined patient groups, including specified spinal cord injuries, post-stroke weakness, and certain progressive neuromuscular diseases. It also includes cerebral palsy in people aged 12 or older and specified forms of spastic paraplegia. Patients need enough residual hip and knee motor and movement-related function to trigger and control the system, so a diagnosis by itself doesn't answer whether HAL will be appropriate for somebody.
The same U.S. labeling describes use with body-weight support, alongside regular physiotherapy, inside healthcare facilities under trained medical supervision. Its intended purpose is to temporarily help improve walking after the training intervention, and it isn't intended for sports or stair climbing. That puts the device in a very different setting from a suit someone buys to wear around town. I find the actual setting interesting in its own right, with the machine serving a particular part of a rehabilitation program while the clinical team works out whether it fits the person in front of them.
HAL Is a Family of Devices
Another thing that can make the story confusing is that HAL refers to several products, so a video of one version doesn't establish what every other version does. Cyberdyne has a single-joint medical system for targeted training, with attachments suited to different joints, as well as lower-limb systems. It also makes a lumbar labor-support version intended to assist movement during tasks such as lifting and carrying, reducing load on the lower back. Those are different jobs, and the manufacturer's Japanese product page identifies the labor-support model as a product available in Japan, rather than an all-purpose medical suit with one worldwide set of uses.
I can see why the work-support branch is appealing, particularly in jobs that involve moving things throughout the day, but I'd want its benefits assessed for the actual task and working conditions. A wearable aid still has to fit into what somebody is doing, how they move, and what other equipment they're using. The medical lower-limb system's clearance doesn't automatically cover a different model, and assistance during lifting doesn't establish that a device prevents every back injury. The family resemblance is interesting, while the details of each version tell us what we can reasonably expect it to do.
The Future Includes Getting to the Appointment
The next part I'd like to hear more about is how a useful machine becomes a practical option for the people who might benefit from it. If someone is considering a course of training, there are ordinary questions about finding an appropriate clinic, getting there, fitting sessions around the rest of life, and understanding what a program would cost. Those questions need answers from the provider and the person's own care team, including what coverage might apply. I can get carried away with the engineering, but eventually somebody has to make the appointment and work out how to get through the door.
I'd also want to know what matters most to the person doing the training, because an improved test result becomes much more meaningful when it connects with something they want to do. That might involve a walking goal, another mobility goal, comfort, endurance, or deciding whether the sessions are worth the effort involved. A wheelchair or another aid can remain part of someone's life while rehabilitation serves a particular purpose, and there's room for those choices to sit together. The wearer gets to have priorities that are more individual than the ending we'd like to give a story about a remarkable robot.
There's Plenty Here to Be Excited About
What stays with me is the possibility of making a machine respond to an effort that would otherwise be difficult to turn into useful movement, then studying what repeated assisted practice might help someone do. That's already an enormous amount of interesting science, from recording a signal at the skin to coordinating motors with a person whose needs may change from one session to another. I can understand why researchers keep returning to it, and why clinicians would want a clear picture of when it helps. I'd happily read considerably more about those adjustments, even if I occasionally need a diagram to keep all the parts straight.
I also like that the idea brings us back to something as familiar as taking a step, after all the sensors and control systems have had their turn in the conversation. The goal somebody cares about might be very ordinary from the outside and enormously important to them, which gives the engineering a useful direction. I'll probaby keep getting distracted by the impressive-looking hardware, because it is an exoskeleton and I am clearly interested, but I'd want to hear the wearer's account as well. What became easier, what still takes work, and whether the experience helped them do something they wanted to do would tell me a great deal about where this technology belongs.
A muscle-anatomy poster would be useful company while I read about how all these movements fit together. Follow one part of the leg, find the next and let a very ordinary walk turn into several more questions.
Related Reads from the Archive
The Nerve Reborn: UCLA’s Breakthrough Drug That Restores Movement After Stroke
AI Tool Maps 3D Chromosome Structures: A New Era of Cellular Cartography
Rewinding Time at the Cellular Level: How Scientists Made Human Skin Cells 30 Years Younger
Will Nanorobots Make Us Immortal by 2030? The Future of Forever
Telomeres and Time: Why Cellular Clocks Matter to Aging and Cancer
CRISPR and the Future of Genetic Editing: A New Era of Human Invention
Sources
University of Tsukuba: Gait kinematics and exoskeleton research
FDA: Medical HAL Lower Limb Type clearance and indications, K233695 (2024)
Nakajima and colleagues: Randomized neuromuscular-disease trial (2021)
Wall and colleagues: Randomized stroke rehabilitation study (2020)
Original Reference Links
This article is for general information, not an individual rehabilitation recommendation. A qualified rehabilitation team can assess suitability, available treatments, and the goals that matter to the person receiving care.
