I have a very practical question for any invention being asked to rescue civilization: will it help pay for childcare? Because an artificial womb is an extraordinary thing to think about, but the baby eventually needs somewhere to live. There are groceries involved. Somebody still has to figure out what happens between the end of the workday and the end of the school day, which seem to have been scheduled by people who have never met.
That is what keeps pulling me back to the conversation about artificial wombs and falling birth rates. The science is fascinating, and the demographic concerns are real in particular places. Put them together, though, and suddenly a technology intended to help extremely premature babies is being handed responsibility for the future of entire countries. That's a rather large additional assignment for a developing medical device.
I wanted to understand where those two stories actually connect. Could making pregnancy safer eventually help people have the families they want? Possibly, depending on what future research makes possible. Could the research being done today reverse population decline? We don't have evidence for that, and the distinction becomes much easier to follow once we look at what an artificial womb is being designed to do.

The World Is Growing and Getting Older at the Same Time
The United Nations' World Population Prospects 2024 projected a global population peak of about 10.3 billion in the mid-2080s, followed by a gradual decline to roughly 10.2 billion in 2100. Those are projections with uncertainty attached. They describe a world that keeps growing for decades, even while individual countries face shrinking populations and substantial changes in their age structure.
The UN's explanation of those projections also puts the familiar replacement figure in context. Around 2.1 births per woman is the benchmark for maintaining a population across generations in low-mortality settings without migration. Falling below that figure doesn't make a country's population disappear on a countdown clock. The ages of people already living there, deaths, and migration all affect what happens next.
I find this helpful because a school district with fewer children and a city trying to build enough classrooms can both exist on the same planet. Their problems need different responses. A global number is useful for understanding the broad picture, but I'd want to know whose population we're discussing before agreeing that everyone needs the same solution.
The UN's discussion of population aging points toward healthcare, long-term care, social protection, and migration as important parts of planning. My own question is how people can keep participating and getting the care they need as communities change. Reducing every older person to an expense and every child to a future taxpayer leaves out most of the reasons we care about either of them.
There Is a Lot of Life Between Wanting a Baby and Raising One
UNFPA's 2025 State of World Population report looked at the gap between the families people want and the families they feel able to have. Its survey with YouGov covered 14 countries, and respondents identified barriers including financial limitations and worries about the future. That is a survey of particular populations, rather than permission to assume that everybody secretly wants four children. People want different lives.
What interests me is how ordinary many of those barriers are. A person can want a child and still be looking at rent, working hours, medical expenses, or the absence of somebody dependable to share the care. Pregnancy can be one substantial part of that calculation. The years after pregnancy occupy quite a bit of space in it too, and they keep turning up long after the exciting announcement.
The OECD's analysis of fertility and family policy examines employment, housing costs, parental leave, and early childhood care together. It describes associations and policy effects that vary with context, rather than one guaranteed way to raise birth rates. A continuous system of support matters because a family can get through parental leave and then discover that affordable childcare has a waiting list with its own geological timeline.
I have a similar interest in the choices behind spending on luxury brands and the very different choices behind changing the flour I use. Those are obviously different stakes, but both get me thinking about what a purchase is supposed to deliver. With parenthood, the gap between a big promise and an everyday need becomes enormous. A technology that changes gestation would still have to fit into a life that someone can manage.
The Medical Goal Is to Give Extremely Premature Babies More Time
Artificial womb is a memorable name for several related research ideas. In the near-term work discussed here, the aim is to support aspects of fetal development after an extremely premature delivery. Complete ectogenesis would mean gestation outside the body from beginning to end. That remains a much larger hypothetical possibility, with developmental stages that the late-gestation support experiments don't cover.
In 2017, researchers at Children's Hospital of Philadelphia published a study of an extrauterine system for premature lambs. They supported animals for up to four weeks using a closed fluid environment and an oxygenator connected through the umbilical vessels. The lambs had already developed inside pregnant ewes before being transferred. Reading that last detail makes the experiment's actual achievement much easier to understand.
CHOP's account of the research describes a team trying to bridge a vulnerable developmental period while organs mature. The system used the fetal heart to drive circulation through the oxygenator, rather than relying on an external blood pump. It was an integrated experimental support system, and the results were preclinical. The transparent enclosure in the photographs is only the most immediately visible part of the engineering.
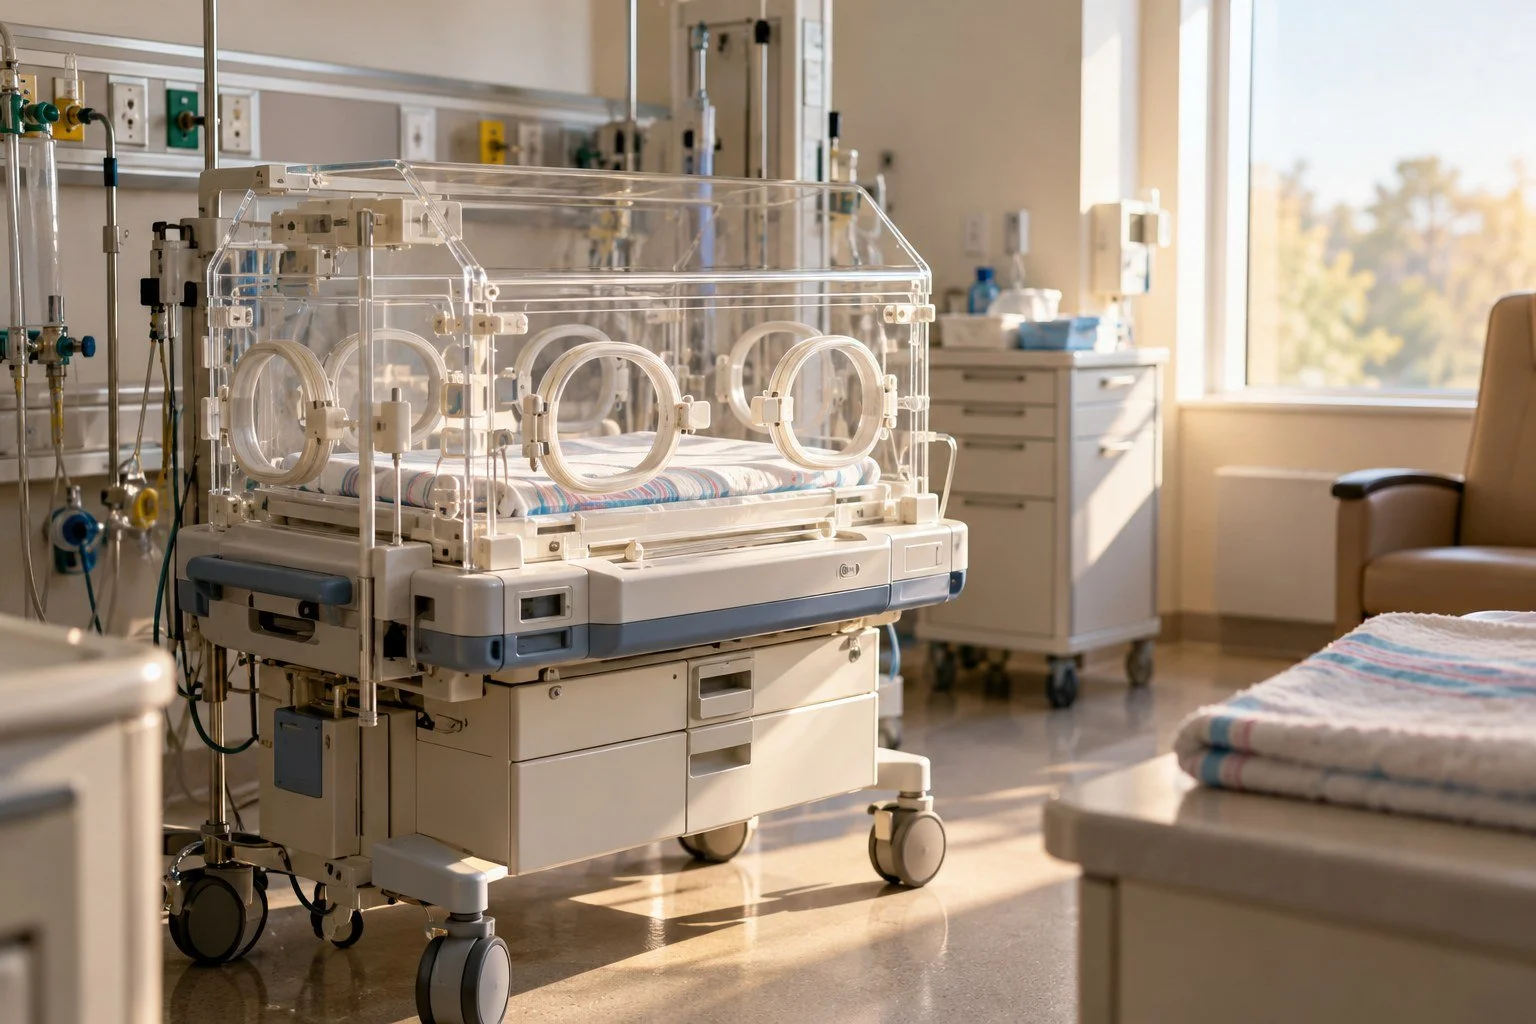
This is also why the conventional incubator in the illustration above needs its proper name. Incubators provide a controlled environment within neonatal care after birth. The experimental systems under discussion seek to maintain aspects of fetal physiology, including fluid around the lungs and an umbilical route for gas exchange. The FDA background presentation explains that intended bridge from extreme prematurity to later development. A familiar-looking clear enclosure can conceal a very different medical task.
The World Health Organization's preterm birth fact sheet estimates that 13.4 million babies were born before 37 completed weeks of pregnancy in 2020. That includes a wide range of gestational ages and care needs. Experimental support for extreme prematurity would concern a subset of those babies, while access to effective existing care remains crucial. The scale of prematurity makes the research compelling without requiring it to solve every kind of premature birth.All this futuristic technology eventually leads back to a little person growing up. A baby milestone photo frame feels like a sweet way to keep those ordinary first-year moments together, the ones a discussion about population numbers can make us forget to picture.
The Lambs, the Mice, and the Trouble With Combining Headlines
Japan's involvement has a longer history than a sudden 2025 breakthrough suggests. A 2017 Tohoku University report describes collaboration with Australian researchers on ex vivo uterine environment therapy, or EVE. The reported work maintained preterm lambs for one week. That is a particular experimental result with a species, a starting stage, and a duration attached to it.
There is also research at much earlier stages. A 2021 mouse embryo study described culture outside the uterus from before gastrulation through a defined stage of organ formation. Those findings concern part of mouse development. Placing that paper beside a late-gestation lamb experiment doesn't produce a single system that can carry a pregnancy all the way through. The space between two impressive milestones still needs its own research.
This is the context I would keep beside my earlier article about Japan and artificial womb research. I want the species and developmental stage before deciding what a success means. A few weeks of support can be a remarkable achievement, while the claim that a mammal has been grown from early gestation through an entire pregnancy requires a different level of evidence. That distinction protects the interesting part of the story from getting buried under a larger promise.
A Research Milestone and an Available Treatment Have Different Jobs
The FDA's September 2023 advisory committee meeting considered how artificial womb technologies should be evaluated, including safety, effectiveness, and ethical questions around first clinical studies. Its stated focus was care for extremely premature infants. That scope matters when someone leaps from a regulatory discussion to the suggestion that prospective parents can start comparing pregnancy pods.
As checked on November 2, 2026, EXTEND developer Vitara Biomedical identifies its technology as investigational and says it has not received market clearance from the FDA or another country's regulatory authority. Its proposed benefits are goals for a developing system. I would keep that current status attached to the company's description, especially when older coverage includes a predicted date for clinical use.
The FDA committee's meeting summary raises questions about animal models, adverse events, informed consent, and follow-up. There isn't a perfect animal model for every feature of a baby's condition. A trial has to consider both what happens while a device is operating and how children fare afterward. Those questions are part of finding out whether a promising approach actually helps families.
I keep returning to that last point because a working machine makes a terrific photograph. A child's development over time requires a much longer story, with careful comparisons and the possibility of disappointing results. I would rather understand the result that researchers have than ask them to supply a happier ending ahead of the data. The hope is substantial enough to survive a precise explanation.

A Future Pregnancy Option Would Still Need a Whole Pathway
If complete gestation outside the body ever became safe and accessible, it could change the options available to people for whom pregnancy poses serious difficulties. That possibility matters. I can understand the interest from people with uterine conditions, from prospective parents who would need other reproductive assistance, and from anyone wondering what a wider range of voluntary choices might look like.
The word if is doing necessary work in that paragraph. Supporting a baby after an extremely premature delivery doesn't establish a way to begin a pregnancy outside the body. It doesn't supply eggs or sperm, resolve every cause of infertility, or establish that every developmental stage can be supported safely. A future option would need evidence across the whole pathway, alongside answers about who could use it and what procedures would be involved.
There would also be a difficult question about who gets to choose. I would want prospective patients and families involved in decisions about access, consent, and acceptable risk. An offer that genuinely expands someone's options should leave them able to decline it. National anxiety about birth rates is a poor reason to treat a person's reproductive decisions as a public resource waiting to be allocated.
I would ask the same questions about cost. Would coverage depend on a medical indication? What would families have to travel for, and who would provide care afterward? Those are hypothetical questions about a hypothetical future option, and they belong in the conversation. Being able to invent something and making it available on fair terms are separate pieces of work.
The Device Cannot Do the Parenting Afterward
Even in a future where pregnancy could happen entirely outside the body, the child would still arrive in a community. A family would need to recieve care, find a home, and arrange the years of support that follow. An artificial womb might address a substantial medical burden for particular people. It would leave the rent standing exactly where it was, probably holding a clipboard.
It would also need trained staff, dependable facilities, and continuing medical support. That makes me cautious about describing a complex investigational system as an immediate answer for places where basic healthcare is difficult to reach. I would want investment in new treatments to sit alongside investment in the care that already helps people. The people who need that care are living through the present while the future is being developed.
The timescale of population policy deserves the same practical attention. A baby born next year will need years of care and education before joining a workforce. Helping families is worthwhile in its own right, while a hospital trying to hire staff now needs responses that can help now. Treating every birth as an immediate fix for a staffing shortage skips most of childhood, which seems like a rather important part of the arrangement.
The Science and the Everyday Questions Belong Together
I enjoy a dramatic science story as much as anyone, whether I'm reading about heightened solar activity or revisiting the Carrington Event. I also want to know what the underlying evidence supports before carrying a headline into the rest of my day. The same habit helps with an extraordinary claim about a farmer finding a gold mine. A compelling premise gives me a reason to read further, followed by several questions.
Even aging wine in space has that familiar pull: take something recognizable, change its surroundings, and see what happens. With reproductive research, the stakes require far more careful evidence and much more attention to the people affected. The interesting question becomes which specific difficulty a technology could address, and whether the improvement is worth the risks and demands involved.
I would welcome a breakthrough that helped a premature baby and family through a difficult beginning. That would be an enormous achievement on its own terms. Alongside the laboratory work, we can ask how to make housing, care, and work more compatible with the families people want. The future can contain an extraordinary new medical option and a much better answer to the perfectly ordinary question of who's picking up the child on Tuesday.
